Abstract
Lipoprotein(a), or Lp(a), is now seen as a major contributor to residual cardiovascular risk, as it is prevalent even in individuals with low levels of low-density lipoprotein cholesterol (LDL-C). Lp(a) combines the structure of an LDL with apolipoprotein A (apo A), which gives rise to a dangerous pathogenic profile. Additionally, its unique characteristics allow it to accelerate plaque formation, oxidised phospholipid-driven inflammation, endothelial dysfunction and thrombosis. These mechanisms highlight why individuals with Lp(a) ≥50 mg/dL experience high rates of myocardial infarction, aortic valve stenosis and stroke despite controlled LDL-C levels. There is a well-established link between Lp(a) concentration and a person’s genetics and ethnicity. Black/African populations exhibit the highest median concentration of Lp(a) at 35.1 mg/dL, followed by White/European ancestry (16-18 mg/dL), Hispanic/Latino, then East Asians.
This further expands the variation of medication needed, personalised to each individual. Current cardiovascular risk management focuses primarily on lowering LDL-C. Through using recent clinical trials and mechanistic studies, this review demonstrates the reasons for testing Lp(a), the mechanistic process behind Lp(a) and future breakthroughs/research. We recognise the genetic causes of elevated Lp(a) and explore how this delays medication initiation as it is a complex process, hence hesitation to start routine testing. Together, these findings underscore Lp(a) as a critical driver of cardiovascular disease (CVD). Therefore, addressing this genetically determined lipoprotein through testing and new therapy options is essential for reducing residual cardiovascular risk.
1. Introduction
Cardiovascular disease (CVD) is a serious problem in the modern world, causing almost 30% of deaths worldwide (Casas et al., 2018). The cardiovascular system contains the heart, blood vessels and blood, and cardiovascular disease can be prevented through lifestyle choices such as dietary patterns and physical activity. Current research into different types of diets shows that, compared to an average Western diet, the Mediterranean diet or other healthier diets are of greater benefit to the cardiovascular system (Casas et al., 2018). The average Western diet often causes an excessive production of proinflammatory cytokines associated with a reduced synthesis of anti-inflammatory cytokines (Casas et al., 2018). This ongoing inflammation damages blood vessels and accelerates the plaque buildup within arteries (Casas et al., 2018) to the detriment of overall cardiovascular health. Alongside poor diet, one of the biggest risks for cardiovascular disease is a sedentary lifestyle, otherwise known as a lifestyle with little to no physical activity (Myers, 2003). While a sedentary lifestyle has many negative effects on cardiovascular health, an active lifestyle has many benefits, including a reduction in blood pressure and low-density lipoprotein cholesterol (LDL-C) and an increase in HDL cholesterol (Myers, 2003). The ideal amount of exercise for the average adult to maintain a healthy cardiovascular system is approximately 30 minutes of moderate exercise most days of the week (Myers, 2003). While these are both good ways to prevent cardiovascular disease, many people still die of it every year. Even with statins and other medications, deaths due to cardiovascular diseases continue to steadily rise (Das & Ingole, 2023).
Lipoproteins are complex particles with a central core containing cholesterol esters and triglycerides surrounded by free cholesterol, phospholipids and apolipoproteins, which facilitate lipoprotein formation and function (Feingold, 2024). Certain lipoproteins have been shown to be associated with cardiovascular disease (Das & Ingole, 2023). For example, LDL is a lipoprotein which causes plaque buildup within arteries (Feingold, 2024). Not all lipoproteins are necessarily harmful (e.g., HDL, the beneficial cholesterol) but some of them do pose a threat to cardiovascular health (Feingold, 2024).
In this research paper, we will be addressing: why physicians should begin to test for lipoproteins instead of LDL-C levels alone; the differences between the testing types; the advantages and disadvantages of both testing types; how lipoproteins are linked with cardiovascular disease; the genetic component of lipoproteins; how lipoproteins affect different ethnicities; the lack of treatment involving lipoproteins; and future research on this topic.
2. Lipoprotein(a) Testing
Current cardiovascular risk testing relies predominantly on LDL cholesterol; however, new research demonstrates that Lp(a) offers superior diagnostic reliability and removes key blind spots in standard screening. Around one in five people have high levels of Lp(a) increasing the risk of a heart attack. Patients of 124 nanomoles per litre or more have a 40% increase in heart attack and stroke risk even when LDL cholesterol is controlled (Kronenberg et al., 2022). This draws attention to the importance of testing for Lp(a) for preventative measures as it is a key component in the development of cardiovascular disease. Lp(a) testing creates a more in-depth view of cardiovascular risk as it calculates the particles holding cholesterol not just the physical amount of cholesterol itself.
Harvard Medical School Associate Professor, Dr. Michelle O’Donoghue, revealed that only 0.3% of people received Lp(a) screening between 2012 and 2019 (Bhatia et al., 2023). Khan details how this lack of testing could be due to decades of subscribing to the idea that a disease that does not have a comprehensive treatment should not be tested for (Khan et al., 2019). This is inaccurate for Lp(a) as extensive treatment can lower its concentration in the blood and, as it is heavily based on genetics, signal potential cardiovascular disease risk in a family, ultimately leading to early prevention. While LDL-C testing has been widely used and studied for the past 50 years (specialists are well trained hence creating a concern to change treatments), new innovation is crucial given that roughly one third of deaths globally are a result of cardiovascular disease, with deaths expected to grow to 24 million annually by 2030 (Soppert et al., 2020).
In a survey conducted by the University of Pennsylvania, health providers were asked whether they request Lp(a) tests. The study involved 571 participants (51.6% female and 48.4% male) and revealed that 69% of clinicians do not routinely order Lp(a) tests. This is crucial as it shows the neglect of testing, with the primary barriers reported as lack of familiarity, lack of evidence/clinical trials and no insurance coverage (D’Souza et al., 2024). However, there was a selection bias that clinicians more familiar/concerned with Lp(a) levels had a tendency to respond, creating a possible fault in results. This survey backs up our concern that there is a lack of Lp(a) testing within healthcare settings.
If we compare LDL cholesterol levels and Lp(a), the main driver behind abnormal LDL cholesterol is diet, lifestyle, exercise and genetics, whereas Lp(a) is almost entirely genetic. This is fundamental as LDL cholesterol levels can fluctuate immensely with lifestyle changes so need to be tested regularly every one to five years. In contrast, Lp(a) remains stable throughout adulthood so a one-time test is sufficient to get lifetime results. This means that testing will be cheaper as only one test per person is needed. Moreover, as it is an inherited trait, if a person has an abnormal Lp(a), their family can be monitored and tested early (i.e., cascade screening) – a key preventive widespread measure that can be implemented.
3. Evidence and Mechanisms by Which Lp(a) Causes Cardiovascular Disease
3.1 Evidence for Lp(a) Causing Cardiovascular Risks
Cardiovascular disease remains a leading cause of morbidity and mortality, despite significant progress in prevention and treatment (Vinci et al., 2023). Even when LDL-C levels are low, having high levels of lipoprotein(a) leaves residual risk for developing CVD (Vinci et al., 2023). Lp(a) has been established as a crucial risk factor responsible for the development of atherosclerotic plaque and various other cardiovascular conditions, including ischemic CVD, aortic valve stenosis (AS), myocardial infarctions (MI) and heart failure (Vinci et al., 2023).
For clinical significance, a threshold of 50 mg/dL of Lp(a) has been established; however, lower levels around 30 mg/dL may still increase risk, as revealed in the INTERHEART study and the Copenhagen City Heart Study (Vinci et al., 2023). These studies also examined the contribution of Lp(a) concentration to MI risk in the general population and found that concentrations of Lp(a) >50 mg/dL were associated with an increased risk. Moreover, epidemiological studies have demonstrated that high levels of Lp(a) increase the risk of aortic valve stenosis, =a condition caused by calcium buildup on the aortic valve. A study conducted in 2013 identified genetic variants in the LPA locus (notably rs10455872) as strongly linked to aortic valve calcification and incident aortic stenosis across multiple ethnic groups (Thanassoulis et al., 2013).
In addition, “large prospective cohort studies and meta-analyses have consistently shown that elevated Lp(a) levels are independently associated with a higher risk of CAD, myocardial infarction, peripheral artery disease and ischemic stroke, even after adjustment for LDL-C and other traditional risk factors” (Granata et al., 2026).
Another distinct example of long-term Lp(a) concentrations correlating with vascular outcomes can be seen when researchers combined data from large, long-term studies that analysed individual records and found that the risk of heart and vascular conditions rises as Lp(a) levels increase; the danger is not limited to those with high Lp(a) but also those with moderate elevations of Lp(a) (Granata et al., 2026). Genetic evidence further strengthens this link, as variants associated with high Lp(a) levels correspond to proportional increases in cardiovascular risk (Granata et al., 2026).
Likewise, contemporary findings suggest that Lp(a) may be more atherogenic (causing arterial plaque buildup) than LDL, as it promotes arterial retention and drives inflammation and thrombosis (Granata et al., 2026). Lastly, patients with premature or recurrent cardiovascular events have been found to have elevated Lp(a), underscoring its role in residual cardiovascular risk. Collectively, these findings highlight Lp(a) as an independent risk factor that requires greater attention with regard to preventing CVD.
3.2 Process of Lp(a) Increasing Cardiovascular Risk
Elevated levels of Lp(a) increase cardiovascular risk through three major biological mechanisms: plaque formation, inflammation and blood clotting. Although the genetic composition of Lp(a) closely resembles that of regular LDL, it differs as it is covalently bound to apolipoprotein(A) (apo A) (Filtz et al., 2026). This variant is a glycoprotein structurally similar to plasminogen, a protein that helps break down clots; this distinctive structure confers a complex pathogenic profile to Lp(a) characterised by proatherogenic, proinflammatory and antifibrinolytic properties (Filtz et al., 2026). In other words, apo A adds several pathogenic properties to Lp(a) which are not present in LDL.
Firstly, Lp(a) contributes heavily to atherogenesis, which is a chronic inflammatory process that leads to the formation of atherosclerotic plaques within arteries: “Lp(a) plays a dual role in inflammation, acting both as a driver and a target of inflammatory signalling” (Filtz et al., 2026). Additionally, Lp(a) contributes to atherogenesis by inducing endothelial activation, thus promoting leukocyte adhesion and enhancing cytokine secretion (Filtz et al., 2026). Several cytokines, including IL-6, regulate LPA gene expression at the transcriptional level, creating a correlation between inflammation and Lp(a) levels (Filtz et al., 2026). In short, Lp(a) accumulates in the arterial wall efficiently due to the binding sites in apo A that promote retention. These characteristics contribute to plaque growth and become increasingly dangerous over time.
Beyond plaque formation, Lp(a) causes oxidative stress, which is attributed to its high burden of oxidised phospholipids (OxPLs) (Filtz et al., 2026). Essentially, OxPLs are molecules that form when cell membranes or lipoproteins undergo oxidative stress; they act as danger signals in the body, triggering immune responses and influencing chronic inflammation (Oskolkova et al., 2022). To clarify, oxidative stress is an imbalance between two molecules (free radicals and oxidants) which results in damage to the body’s cells and tissues; this can trigger plaque to form, thus leading to atherosclerosis and eventually CVD (Cleveland Clinic, 2024). Subsequently, OxPLs induce the production of reactive oxygen species in both endothelial cells and macrophages. In turn, the stress results in: lipid peroxidation, which weakens the cell membrane; protein modification, which disrupts normal function; and DNA damage. These interconnected changes drive endothelial dysfunction and vascular inflammation (Filtz et al., 2026). Endothelial dysfunction is problematic as it causes the thin layer of cells inside blood vessels to constrict, hence triggering coronary artery disease (Cleveland Clinic, 2022). Imaging studies, including PET/CT imaging, further demonstrate that high levels of Lp(a) show greater arterial inflammation (Filtz et al., 2026). Simply put, the presence of OxPLs in Lp(a) leads to inflammation in artery walls due to oxidative stress.
As previously mentioned, Lp(a) contains apo A, which resembles plasminogen. This similarity causes Lp(a) to compete with plasminogen, thereby interfering with normal clot breakdown. Meanwhile, it also increases other clot-promoting factors, leading to dense clots that impair normal blood flow. This is significant as resistant clots increase the risk of stroke and MI as they block blood flow over an increased period of time.
Together, these biological mechanisms provide an explanation as to why Lp(a) increases risk levels for myocardial infarctions and other cardiovascular conditions even when LDL levels are low.
4. Lp(a) Across Ancestry, Genetic Architecture and Causes of Concentration Alterations
Though sharing an identical core structure with LDL, Lp(a) behaves very differently compared with LDL, including how Lp(a) responds to treatments, how it is cleared from the body and how its concentration shifts. Lp(a) concentration is established early in life and remains relatively stable across most of adulthood, but that does not imply that Lp(a) cannot be biologically altered: kidney and liver disease, nephrosis, thyroid status, pregnancy, oestrogen therapy, inflation, diet composition and selected drugs can materially alter measured values (Kronenberg et al., 2022; Reyes-Soffer et al., 2021).
4.1 Why Does Lp(a) Differ by Ancestry/Ethnicity?
The concentration of Lp(a) is predominantly influenced by cis-acting variation at the Lp(a) locus, rather than by trans-acting or environmental factors (Coassin & Kronenberg, 2022; Tsimikas & Marcovina, 2022). The frequency, size and combination of these Lp(a) variants differ substantially by ancestral population.
The trans-ethnic variation can be explained through three interconnected hereditary components:
1. Kringle IV type-2 (KIV-2) copy-number variation: a highly polymorphic, ~5.5 coding repeat within the Lp(a) locus that ranges from fewer than six to more than 40-50 copies, generating 40+ well-defined apo A protein isoforms. Studies have shown that carriers of small isoforms (<= 22 KIV repeats) have median Lp(a) concentrations up to five times higher than carriers of large isoforms (>22 KIV repeats). The variance in plasma Lp(a) levels within a population can alone be explained through isoform size, affecting roughly up to 40-70% of the result (Coassin & Kronenberg, 2022).
2. Single-nucleotide variants (SNVs) in and around KIV-2 and elsewhere in Lp(a) act substantially autonomously of isoform size. It can either amplify or suppress Lp(a) production per isoform and show dramatically different allele frequencies across ancestries (Coassin & Kronenberg, 2022).
3. Ancestry-specific linkage disequilibrium (LD) and haplotype structure, which dictates how isoform size and specific SNVs jointly segregate. This explains why even though different populations may have the same Lp(a) single-nucleotide polymorphism (SNP), it can appear to have different effects on Lp(a) because it may be paired with different apo A isoforms or other variants (Coassin & Kronenberg, 2022).
4.2 Which Population Groups Have the Highest to Lowest Lp(a)?
Multiple large multi-ethnic cohort studies and reviews coalesce on a consistent rank order of Black/African-ancestry population with the highest Lp(a), followed by South Asians, then White/Europeans, then Hispanics/Latinos, with East Asians generally lowest.
Black/African-ancestry populations
Throughout multiple studies, the Black/African-ancestry population invariably displayed the highest population Lp(a) levels across nearly every cohort evaluated to date. The median Lp(a) levels among the Black/African-ancestry participants was 35.1 mg/dL, while Caucasian and Hispanic participants’ median Lp(a) level was ~12.9-13.1 mg/dL (Guan et al., 2015). The findings of the UK Biobank also co-oscillate with that of the Multi-Ethnic Study of Atherosclerosis (MESA), showing the median Lp(a) of Black participants to be the highest amongst all the other cohorts with ~30 mg/dL (Reyes-Soffer et al., 2024).
South Asian populations
South Asian populations are consistently ranked second-highest globally. While specific statistics may vary depending on the cohort, the overall median Lp(a) level for South Asians typically falls between ~17-22 mg/dL (MacDonald et al., 2023) South Asian populations also show a roughly even split between large and small isoforms (Tsimikas & Marcovina, 2022).
White/European-ancestry populations
The White/European-ancestry populations occupy an intermediate position in most rankings with a median Lp(a) of roughly ~16-18 mg/dL. Even within Europe, some gradients persist. The Finnish population, for example, have approximately 50% lower Lp(a) than Central Europeans within every isoform-size stratum, credits given to their distinct KIV-2 subtype frequencies and specific mutational variants such as the splice-site mutation rs143431368. The splice-site mutation of rs143431368 is roughly ten times more frequent in the Finnish population than in non-Finnish Europeans (Coassin & Kronenberg, 2022).
Hispanic/Latino populations
Just under the White/European-ancestry cohort, the Hispanic/Latino populations show a consistent intermediate to low Lp(a), but with substantial diversity by national/regional origins. The Hispanic/Latino populations have an overall median Lp(a) of ~8-12 mg/dL, though Dominican populations can be a distinct exception (Joshi et al., 2023 ).
East Asian populations
Following the Hispanic/Latino population, East Asian populations are consistently the lowest group globally. INTERHEART claims Chinese participants had the lowest median Lp(a) of about 7.8 mg/dL and the largest median apo A isoform size of all seven groups studied within their research (Paré et al., 2019). Along with INTERHEART, the UK Biobank further backs these findings with the median Lp(a) of 6.5 mg/Dl, also the lowest of the ancestry groups reported (Reyes-Soffer et al., 2024). East Asians generally have lower Lp(a) due to a higher frequency of large apo A isoforms and fewer high-risk Lp(a) variants (Kim & Kim, 2025).
4.3 How Much of the Ethnic Variation is Genetic?
Lp(a) concentration is roughly 70-90% heritable within populations; the Lp(a) locus can be held accountable for the overwhelming majority of this heritability (Reyes-Soffer et al., 2021). Isoform size and specific variants and their contributions are listed below:
- 40-70% of Lp(a) variance within a population heavily relies on apo A isoform size (KIV-2 copy number) (Coassin & Kronenberg, 2022; Reyes-Soffer et al., 2024).
- Within European-ancestry populations, the genetic variant rs10455872 roughly represents 25% of Lp(a) variance and is correlated with roughly a +30 mg/dL increase per allele; its minor allele frequency (MAF) is ~6.9% in non-Finnish Europeans but infrequent, about <1%, within African-ancestry populations (Coassin & Kronenberg, 2022).
- The Lp(a) genetic variant rs3798220 is associated with higher Lp(a); throughout the population where the genetic variant is present, it explains approximately 8% of the variation in Lp(a). This specific variant’s frequency differs substantially among the ancestral population: absent in Africans, rare in Europeans (~2%), 12% in South Asians and very frequent in some Hispanic populations with up to 42% MAF (Coassin & Kronenberg, 2022).
- The KIV-2 splice-site variant 4925G>A, which is ~13% prevalent within NFE, decreases Lp(a) by ~31 mg/dL in low-molecular-weight (LMW) isoform carriers, demonstrating the effects of genetic variations on isoform size on Lp(a) levels (Coassin & Kronenberg, 2022).
- The LPA variant KIV-2 splice-site variant 4733G>A has been described as the single strongest genetic contributor to Lp(a) variance within the Caucasian population only after isoform size itself. The MAF is about 22% and can increase up to 38% carrier frequency (Coassin & Kronenberg, 2022). The variant reduces Lp(a) by ~30 mg/dL; however, when paired with the 4925G>A variant, it reduces Lp(a) by 31.8 mg/dL and narrows the interquartile range to approximately nine-fold (Coassin & Kronenberg, 2022).
- About 14% of Lp(a) in Europeans can be explained by the promoter pentanucleotide repeat (PNR) region, a specific stretch of DNA that is located inside a gene’s promoter with a structure of a “short tandem repeat”; this region is prone to frequent mutations. Though a relative association can be correlated within the European population, studies show no significant association in Black/African populations (Coassin & Kronenberg, 2022).
- rs1853021 is associated with lowering Lp(a) specifically in African-ancestry populations by ~10 mg/dL; this effect is suppressed in White populations due to linkage disequilibrium with isoform size (Coassin & Kronenberg, 2022).
- Associating with a 40-60% relative increase in Lp(a), the rs1800769 genetic variant is commonly seen amongst African-ancestry populations; this suggests that higher Lp(a) within the African-ancestry population is not entirely determined through different isoform sizes: additional genetic variants can contribute as well (Coassin & Kronenberg, 2022).
4.4 What Can Cause Alterations in the Concentration of Lp(a)?
Unlike LDL-cholesterol, Lp(a) is minimally responsive to diet, exercise and standard lifestyle modifications. Though Lp(a) is minimally responsive, several conditions can still alter Lp(a) levels. Reduced renal clearance of the kidney is associated with elevated Lp(a) due to the fact that healthy kidneys help filter, breakdown and clear Lp(a) particles from the bloodstream; therefore, a reduction on the renal clearance of the kidney will fail to clear Lp(a) particles from the bloodstream. Reduced liver functions are also associated with an effect on Lp(a) levels. Since apolipoprotein(A) is synthesised exclusively in the liver, if the function decreases, it will decrease the apo A synthesis and, in turn, will also decrease Lp(a) levels (Shapiro et al., 2025).
Such health implications are not the only factors that can influence Lp(a) levels to a certain degree. Below, a table of other conditions and their effect(s) on Lp(a) is given.
| Condition/Intervention | Effect on Lp(a) |
| Replacement of dietary saturated fat with carbohydrate/unsaturated fat | ~10-15% increase |
| Low-carbohydrate diet high in saturated fat | ~15% decrease |
| Fasting | None |
| Physical activity | None/minimal |
| Hyperthyroidism | Decrease; 20-25% increase with thyrostatic treatment/RAI therapy |
| Hypothyroidism | Increase; 5-20% decrease with replacement therapy |
| Growth hormone therapy | ~2-fold increase |
| Endogenous sex hormones | None/minimal |
| Pregnancy | ~2-fold increase |
| Menopause | None/minimal |
| Postmenopausal hormone replacement therapy | ~25% decrease |
| Surgical/biochemical castration (males) | Small increase |
| Ovariectomy/oestrogen receptor antagonist | Small increase |
| Nephrotic syndrome | 3-5-fold increase vs. controls |
| Peritoneal dialysis | 2-fold increase vs. controls |
| Haemodialysis/CKD | Increases, mainly in large apo A isoform carriers |
| Kidney transplantation | Approximate normalisation |
| Hepatic impairment | Decrease, depending on cause |
| Liver transplantation | Apo A isoform switches to donor’s, with corresponding Lp(a) |
| Severe acute-phase conditions (sepsis, burns) | Decrease |
| Several chronic inflammatory conditions | Increase |
| Tocilizumab (IL-6 inhibitor) | ~30-40% decrease |
| Protease inhibitors/antiretroviral therapy | Increase |
| Statins | May slightly increase (heterogeneous reports) |
| Air pollution (PM2.5) | Slight increase |
Table 1. Medical, environmental and environmental conditions and their effect(s) on Lp(a) (Kronenberg et al., 2022).
5. Current Lp(a) Targeted Treatments That Mitigate Residual Cardiovascular Risk
Although a well-known connection exists between high levels of Lp(a) and cardiovascular disease, addressing this issue in clinical practice remains difficult. This is mainly because standard lipid-lowering treatments have little effect on Lp(a) levels. For example, statins, commonly used to lower low-density lipoprotein cholesterol, have little effect on Lp(a) and may even increase it. Data from JUPITER showed a 10%-20% increase in plasma Lp(a) levels in patients treated with rosuvastatin (Khera et al., 2014), showing that Lp(a) levels remain a significant determinant of residual cardiovascular risk, even in patients who have achieved low LDL targets. A similar study of 3896 patients on various statins showed mean Lp(a) levels increased by 11% and Oxpl-apob levels increased by 24% (Khera et al., 2014). Consequently, these findings demonstrate that statins cannot manage, and may even cause, hyperproteinemia(a), a high level of Lp(a) in the blood, emphasising the urgency to develop treatments that safely lower Lp(a) concentrations.
Niacin has played a pivotal role in the management of Lp(a) levels, being one of the few drugs capable of directly lowering lipoprotein(a) levels. Research has shown that niacin suppresses the transcriptional activity of the LPA gene promoter, which encodes apolipoprotein(a), playing a role in the regulation of Lp(a) levels. Furthermore, niacin may also affect the production of apolipoprotein B100 (apo B100), an essential component of lipoprotein(a) (Galal et al., 2025). Several studies have shown that using niacin alone, or combined with other statins, can decrease Lp(a) levels by as much as 30-40%, depending on the dosage. Niacin may also lower LDL cholesterol, total cholesterol, triglycerides and remnant cholesterol, while increasing HDL cholesterol. (Nordestgaard et al., 2010). A case study showed a 62-year-old man with coronary artery disease, a calcium score of 254 and high Lp(a) levels came for a cardiology evaluation. His Lp(a) was 325.7 nmol/L, and he was not on any lipid-lowering medication. He started high-dose rosuvastatin, but after six months, his Lp(a) was still high at 313 nmol/L, a reduction of only 3.9%. When 500 mg of niacin daily was added, his Lp(a) dropped to 115 nmol/L, a 63% reduction after five months (Al-Kindi et al., 2023). While high doses of statins failed to lower Lp(a) levels, niacin was able to significantly reduce them, proving its clinical effectiveness in lowering Lp(a) concentrations.
Lipoprotein apheresis is currently the most effective way to lower high Lp(a) levels and improve clinical outcomes. This procedure removes lipoproteins containing apo B100 from plasma or whole blood, reducing harmful atherogenic lipoproteins by more than 50% (Vinci et al., 2023). Techniques include dextran sulfate cellulose adsorption (DSA), heparin-induced extracorporeal LDL cholesterol precipitation (HELP), immunoadsorption, double filtration plasmapheresis (DFPP) and direct adsorption of lipoproteins (DALI) (Franchini et al., 2016). In systems such as DSA, HELP, immunoadsorption and DFPP, plasma is separated from red blood cells before LDL cholesterol and Lp(a) are removed. In contrast, the DALI method removes these lipoproteins directly from whole blood (Franchini et al., 2016). Data on apheresis shows a 60-70% reduction in LDL-C and Lp(a) concentrations and a 54-90% reduction in cardiovascular events (Vinci et al., 2023). This significant decrease in Lp(a) concentration emphasises the effectiveness of apheresis as a treatment for hyperlipoproteinemia(a). In addition, a Russian study of 30 patients with coronary heart disease compared apheresis to statin therapy. In addition to a 73% drop in Lp(a), apheresis also reduced the median percent diameter stenosis and increased the minimal lumen diameter more than statin treatment did. These findings suggest that lipoprotein apheresis may help reverse coronary atherosclerosis in patients with stable heart disease and high Lp(a) levels (Liao et al., 2013, as cited in Sadeghi et al., 2016).
5.1 Evaluating the Future Direction and Testing of Therapies to Lower Lp(a) Levels
Until recently, there has not been a viable and tested therapy that can adequately lower Lp(a) levels. Without viable therapies, clinicians rarely test a patient’s Lp(a) levels as elevated levels do not lead to a direct change in targeted medical treatment (Al-Dalakta et al., 2025). Statins, ezetimibe and radical prescribed lifestyle changes have long been the method for lowering LDL-C levels but fail to target or improve Lp(a). While still in testing, innovative therapies such as Olpasiran, Lepodisiran, Muvalaplin and Pelacarsen have created a reduction in levels of Lp(a) in ways that previously seemed impossible, raising the question: does lowering Lp(a) levels actually reduce the risk of cardiac events such as heart attacks and strokes? When considering each of these drugs, researchers must first consider whether the drug is safe, ask whether it lowers the Lp(a) levels and decide whether lowering levels will have a substantial impact on patient health. These are the three layers of analysis that these trials aim to answer and will determine the future of how we treat those suffering from high Lp(a).
Among all of the therapies now being developed to lower Lp(a) levels, one has moved further through clinical testing and approval above any other: Pelacarsen, developed by Ionis Pharmaceuticals. Unlike other therapies that aim to reduce exisiting Lp(a) within the bloodstream, Pelacarsen works by targeting the messenger RNA that is responsible for creating apolipoprotein(a), which effectively reduces the body’s ability to synthesise Lp(a) (Smith, 2026). Apolipoproteins are the protein component that makes Lp(a) structurally distinct from ordinary LDL so silencing it would interfere with the production of Lp(a). It is administered as a monthly subcutaneous injection and has shown reductions in Lp(a) of up to 80% in earlier-phase trials (Corliss, 2025). At the time of writing, Pelacarsen is in stage three of the Lp(a) HORIZON trial, one of the most advanced clinical trials in the medical industry that is researching and investigating Lp(a) reduction.
According to the Family Heart Organisation, the HORIZON trial will be “the first to test the hypothesis that significantly lowering Lp(a) reduces cardiovascular events” (Smith, 2026). The trial is the largest Lp(a) trial in the world, in its third phase, which operates as a randomised, placebo-controlled trial in hopes of more accurate results, enrolling 8,323 patients that have cardiovascular disease and elevated Lp(a) levels (Cho et al., 2025). This HORIZON trial makes Pelacarsen a particularly influential test case, not just for the drug itself, but for other therapies, clinicians, patients and other stakeholders alike. Its results will be the first real evidence for the medical industry of whether lowering Lp(a) will physically translate into fewer heart attacks and strokes, or whether there will be continued residual effects of high Lp(a) on the heart and the rest of the cardiovascular system.
While Pelacarsen has moved the furthest through clinical testing, it is not the only drug currently in development to lower Lp(a). Olpasiran, developed by Amgen, works through a similar gene-silencing approach to block the production of apo A proteins that are created in the liver. While Pelacarsen utilises antisense oligonucleotides to block the production of apo A by binding to the mRNA responsible for producing it, Olpasiran uses siRNA, which achieves a similar outcome by using double stranded synthetic DNA to bond to the mRNA. This is used as part of a much larger genetic signalling sequence, outlined in Figure 1, that effectively highlights apo A mRNA as the target for degradation. Early trials have shown even greater reductions in Lp(a), with some data showing levels dropping by more than 95% (O’Donoghue et al., 2022).
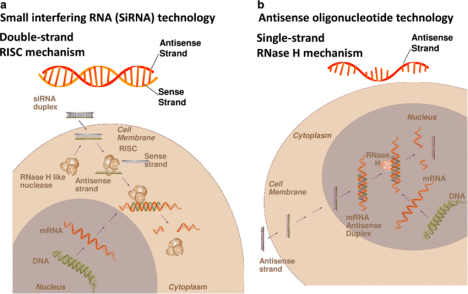
Figure 1. The differences between Olpasiran’s (a) and Pelacarsen’s (b) drug technologies (Langsted & Nordestgaard, 2019).
Olpasiran is currently being tested in the OCEAN(a) trial, managed by Amgen and the TIMI Study Group, to determine whether the lowering of Lp(a) in the bloodstream correlates to a reduction in risk of cardiovascular events with patients who use said drug. While the drug has had massive success within stage 2 (the OCEAN(a)-DOSE trial), achieving a 95% success rate at lowering Lp(a) in the bloodstream, stage 3 (the OCEAN(a)-Outcome trial) is still testing “the effect of treatment with Olpasiran, to placebo, on the risk for coronary heart disease death” (Amgen, 2026). This is the very same question that the HORIZON trial is also trying to answer.
Lepodisiran, developed by Eli Lilly, works in a similar way, but the ACCLAIM-Lp(a) trial is not expected to be completed until 2029, making it the furthest away from any real-world answer. Muvalaplin, also from Eli Lilly, utilises a different mechanism: rather than targeting mRNA in the liver, it works as a small molecule that physically blocks apo A from binding to LDL particles in the first place, stopping a complete Lp(a) particle from ever forming. Unlike the other three treatments, which all require injections ranging from monthly to quarterly, Muvalaplin could eventually be taken as a daily pill, which may end up being one of its biggest advantages.
Ultimately, the future of Lp(a) treatment will not be determined by which drug lowers levels the most, but by which trial, if any, is the first to prove that doing so actually improves patient outcomes. For example, while Olpasiran has a success rate of 95% at lowering Lp(a) levels, rivalling Pelacarsen’s 80% success rate, the outcomes portion of each trial remains one of the most important factors in determining real clinical benefit. Until HORIZON(a) and other following trials, such as OCEAN(a), report their results, the true impact of this new class of therapies will remain unknown.
6. Conclusion
In conclusion, Lp(a) is an often overlooked and important risk factor for cardiovascular disease. High Lp(a) levels come with an increased risk of serious cardiovascular events, such as strokes and myocardial infarctions. Lp(a) has also been associated with cardiovascular risks and long-term damage to the heart and blood vessels (Nordestgaard et al., 2010). This makes Lp(a) an important factor to consider when screening for cardiovascular health. While measuring for regular LDL cholesterol tests is still important, it may be more effective to broaden the testing to include Lp(a) testing.
One of the biggest concerns with Lp(a) is that it can affect someone who may otherwise appear to have healthy cholesterol levels. A person may have low or normal cholesterol and still have elevated Lp(a) levels. This means that testing solely for LDL levels may fail to identify high Lp(a) that puts the person at risk. One in five people are estimated to have high Lp(a) levels but few are ever tested. Increasing the use and availability of Lp(a) testing could help identify patients with increased genetic risk.
The future of Lp(a) testing and treatment is promising. While there are few options currently that are capable of directly lowering Lp(a) levels a substantial amount, new medications in development could help lower Lp(a) levels and initiate an important change in how cardiovascular disease is treated and prevented. Although the relationship between high Lp(a) and cardiovascular disease is well established, lowering Lp(a) levels will provide further clarity about its contributions to cardiovascular events. The results of ongoing and future research could help prove whether lowering Lp(a) levels results in fewer strokes, myocardial infarctions and other forms of cardiovascular damage.
Ultimately, we believe Lp(a) deserves much more attention from both researchers and healthcare professionals. Its genetic nature, ability to increase risk even when LDL-C is low and prevalence among the population make it an important but overlooked cardiovascular risk factor. Greater awareness and more widespread testing could help identify people at risk for cardiovascular damage, and the therapies starting to become available could potentially lower that risk. As research continues, focusing more on Lp(a) could lead to a better understanding of cardiovascular disease and more effective ways to prevent serious cardiovascular events.
Bibliography
Al-Dalakta, A., Cho, L.S. & Sarraju, A. (2025) Lipoprotein(a) in clinical practice: what clinicians need to know, Cleveland Clinic Journal of Medicine, 92(11), pp. 679–686.
American Heart Association (2026) Lipoprotein(a), American Heart Association [online]. <https://www.heart.org/en/health-topics/cholesterol/genetic-conditions/lipoprotein-a>
Amgen (2026) Olpasiran trials of cardiovascular events and lipoprotein(a) reduction – outcomes trial (OCEAN(a)-Outcomes), National Library of Medicine, NCT05581303 [online]. <https://clinicaltrials.gov/study/NCT05581303>
Bhatia, H.S., Hurst, S., Desai, P., Zhu, W. & Yeang, C. (2023) Lipoprotein(a) Testing Trends in a Large Academic Health System in the United States, Journal of the American Heart Association, 12(24), e031255.
Camaré, C., Pucelle, M., Negre-Salvayre, A. & Salvayre, R. (2017) Angiogenesis in the atherosclerotic plaque, Redox Biology, 12, pp. 18–34.
Casas, R., Castro-Barquero, S., Estruch, R. & Sacanella, E. (2018) Nutrition and Cardiovascular Health, International Journal of Molecular Sciences, 19(12), 3988.
Cho, L., Nicholls, S.J., Nordestgaard, B.G. et al. (2025) Design and rationale of Lp(a)HORIZON trial: assessing the effect of lipoprotein(a) lowering with pelacarsen on major cardiovascular events in patients with CVD and elevated Lp(a), American Heart Journal, 287, pp. 1–9.
Cleveland Clinic (2022) Endothelial Dysfunction, Cleveland Clinic [online]. <https://my.clevelandclinic.org/health/diseases/23230-endothelial-dysfunction>
Cleveland Clinic (2024) Oxidative Stress, Cleveland Clinic [online]. <https://my.clevelandclinic.org/health/articles/oxidative-stress>
Coassin, S. & Kronenberg, F. (2022) Lipoprotein(a) beyond the kringle IV repeat polymorphism: The complexity of genetic variation in the LPA gene, Atherosclerosis, 349, pp. 17–35.
Corliss, J. (2025) Lipoprotein(a): an update on testing and treatment, Harvard Health Publishing [online]. <https://www.health.harvard.edu/heart-health/lipoproteina-an-update-on-testing-and-treatment>
Das, P. & Ingole, N. (2023) Lipoproteins and Their Effects on the Cardiovascular System, Cureus, 15(11).
D’Souza, J., Bajaj, A. et al. (2024) Attitudes and barriers to lipoprotein(a) testing: A survey of providers at the University of Pennsylvania Health System, Journal of Clinical Lipidology, 18(5), e873–e876.
Feingold, K.R. (2024) Introduction to Lipids and Lipoproteins, National Library of Medicine [online]. <https://www.ncbi.nlm.nih.gov/books/NBK305896/>
Filtz, A., Slipczuk, L. & Gulati, M. (2026) Presumed Mechanisms Underlying Lipoprotein(a)-caused Atherosclerosis, European Cardiology Review, 21, e07.
Franchini, M., Capuzzo, E. & Liumbruno, G.M. (2016) Lipoprotein apheresis for the treatment of elevated circulating levels of lipoprotein(a): a critical literature review, Blood Transfusion, 14(5), pp. 413–418.
Galal, A.R.M., Salah, M.A.R., Binsaleh, A.Y. et al. (2025) Targeting cardiovascular and metabolic risk modification in end stage renal disease (ESRD): a randomized controlled clinical trial on niacin’s effects on lipoprotein(a) and biochemical markers in hemodialysis patients, Frontiers in Medicine, 12, 1625417.
Ginsberg, H.N. (1998) Lipoprotein Physiology, Endocrinology and Metabolism Clinics of North America, 27(3), pp. 503–19,
Granata, L.G., Giubilato, S., Campanella, F. et al. (2026) Lipoprotein(a) in cardiovascular disease: pathophysiology, residual risk, and emerging therapeutic strategies, Frontiers in Medicine, 13.
Guan, W., Cao, J., Steffen, B.T., Post, W.S. et al. (2015) Race is a key variable in assigning lipoprotein(a) cutoff values for coronary heart disease risk assessment: the Multi-Ethnic Study of Atherosclerosis, Arteriosclerosis, Thrombosis, and Vascular Biology, 35(4), pp. 996–1001.
Ionis Pharmaceuticals (2019) Ionis announces enrollment completion of Phase 3 Lp(a) HORIZON cardiovascular outcomes study of pelacarsen, Ionis Pharmaceuticals [online]. <https://ir.ionis.com/news-releases/news-release-details/ionis-announces-enrollment-completion-phase-3-lpa-horizon>
Joshi, P.H., Marcovina, S., Orroth, K., López, J.A.G. et al. (2023) Heterogeneity of Lipoprotein(a) Levels Among Hispanic or Latino Individuals Residing in the US, JAMA Cardiology, 8(7), pp. 691–696.
Khan, N., Khan, A. & Sperling, L.S. (2019) Lipoprotein(a): the underutilized risk factor for cardiovascular disease, Vascular Health and Risk Management, 15, pp. 499–507.
Khera, A.V., Everett, B.M., Caulfield, M.P. et al. (2014) Lipoprotein(a) concentrations, rosuvastatin therapy, and residual vascular risk: an analysis from the JUPITER trial, Circulation, 129(6), pp. 635–642.
Kim, J.A. & Kim, N.H. (2025) Lipoprotein(a) and Cardiovascular Risk in Asian Populations: A Comprehensive Review, Journal of Lipid and Atherosclerosis, 14(2), pp. 174–187.
Kronenberg, F., Mora, S., Stroes, E.S. et al. (2022) Lipoprotein(a) in health and disease: from biology to clinical practice, European Heart Journal, 43(39), pp. 3925–3946.
Kronenberg, F., Mora, S., Stroes, E.S. et al. (2022) Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement, European Heart Journal, 43(39), pp. 3925–3946.
Landray, M.J., Haynes, R., Hopewell, J.C. et al. (2014) Effects of extended-release niacin with laropiprant in high-risk patients (HPS2-THRIVE), The New England Journal of Medicine, 371(3), pp. 203–212.
Langsted, A. & Nordestgaard, B.G. (2019) Antisense oligonucleotides targeting lipoprotein(a), Current Atherosclerosis Reports, 21(7), 30.
MacDonald, M. (2023) Lipoprotein(a) and ethnicity: why your background matters, Dr Mike MacDonald [online]. <https://drmikemacdonald.com/exploring-lipoprotein-a-diversity-among-ethnicities/>
Myers, J. (2003) Exercise and Cardiovascular Health, Circulation, 107(1).
Nordestgaard, B.G., Chapman, M.J., Ray, K., Boren, J. et al. (2010) Lipoprotein(a) as a Cardiovascular Risk Factor: Current Status, European Heart Journal, 31(23) pp. 2844–53.
O’Donoghue, M.L., Rosenson, R.S., Gencer, B. et al. (2022) Small interfering RNA to reduce lipoprotein(a) in cardiovascular disease, New England Journal of Medicine, 387(20), pp. 1855–1864.
Oskolkova, O.V., Birukova, A.A., Birukov, K.G. & Bochkov, V.N. (2022) Oxidized phospholipids are biomarkers, drug targets, and drug leads, Frontiers in Drug Discovery, 2.
Paré, G., Çaku, A., McQueen, M., Anand, S.A. et al. (2019) Lipoprotein(a) Levels and the Risk of Myocardial Infarction Among 7 Ethnic Groups, Circulation, 139(12), pp. 1472–1482.
Reyes-Soffer, G., Ginsberg, H.N., Berglund, L. et al. (2022) Lipoprotein(a): A Genetically Determined, Causal, and Prevalent Risk Factor for Atherosclerotic Cardiovascular Disease: A Scientific Statement From the American Heart Association, Arteriosclerosis, Thrombosis, and Vascular Biology, 42(1), e48–e60.
Reyes-Soffer, G., Yeang, C., Michos, E.D., Boatwright, W. & Ballantyne, C.M. (2024) High lipoprotein(a): Actionable strategies for risk assessment and mitigation, American Journal of Preventive Cardiology, 18, 100651.
Shapiro, M.D., Haddad, T.M., Weintraub, H.S. et al. (2025) Lipoprotein(a) levels in a population with clinical atherosclerotic cardiovascular disease in the United States: A subanalysis from the Lp(a)HERITAGE study, Journal of Clinical Lipidology, 19(1), pp. 28–38.
Smith, M. (2026) Ongoing clinical trials targeting lipoprotein(a), Family Heart Foundation [online]. <https://familyheart.org/lpa-clinical-trials>
Soppert, J., Lehrke, M., Marx, N., Jankowski, J. & Noels, H. (2020) Lipoproteins and lipids in cardiovascular disease: from mechanistic insights to therapeutic targeting, Advanced Drug Delivery Reviews, 159, pp. 4–33.
Thanassoulis, G., Campbell, C.Y., Owens, D.S. et al. (2013) Genetic Associations with Valvular Calcification and Aortic Stenosis, New England Journal of Medicine, 368(6), pp. 503–512.
Tsimikas, S. & Marcovina, S.M. (2022) Ancestry, Lipoprotein(a), and Cardiovascular Risk Thresholds: JACC Review Topic of the Week, Journal of the American College of Cardiology, 80(9), pp. 934–946.
Vinci, P., Di Girolamo, F.G., Panizon, M. et al. (2023) Lipoprotein(a) as a Risk Factor for Cardiovascular Diseases: Pathophysiology and Treatment Perspectives, International Journal of Environmental Research and Public Health, 20(18), 6721.