Introduction
Post-traumatic stress disorder (PTSD) is mainly caused by an extreme, unexpected event that is perceived as life-threatening, ultimately having an intense impact on the senses of the person involved (Hordvik, 2019). PTSD can occur after a single traumatic event or a series of traumatic experiences that involve actual or threatened death, serious injury or sexual violence (Mental Health Centre, 2026). PTSD triggers can be classified into “acute” and “chronic” trauma, where chronic trauma is more likely to develop into C-PTSD than acute triggers. Chronic PTSD, also known as Complex Post-Traumatic Stress Disorder (C-PTSD) is a severe mental illness recently defined in the International Classification of Diseases 11th edition (Mok, Douflias & Lena, 2025). C-PTSD develops in response to prolonged, repeated or interpersonal trauma, often occurring over months or years. The primary distinction between PTSD and C-PTSD lies in the trauma and the scope of symptoms. PTSD is often associated with a specific event or set of events, whereas complex PTSD is linked to ongoing trauma that shapes development and identity over time (Mental Health Centre, 2026). C-PTSD has the clinical features of PTSD and symptoms that reflect the prolonged impact of sustained trauma on self-organisation, encompassing affect regulation, negative self-concept and difficulties sustaining interpersonal relationships (Stubley, Chipp & Buszewicz, 2025).
Children experience high rates of potentially traumatic experiences (Cohen & Scheeringa, 2009), and many subsequently develop mental health problems, including PTSD. However, PTSD in children frequently varies in presentation compared to adults, making diagnosis more challenging (Hendren & McCarthy, 2009). This is largely due to trauma in children differing greatly from adult responses, as they lack the vocabulary or emotional awareness to articulate their emotions. Consequently, adults may misinterpret trauma-related behaviours, such as aggression, withdrawal or others, as behavioural problems rather than manifestations of PTSD (Hordvik, 2019; PTSD UK, n.d.). Moreover, children may lack the maturity to understand the reason for mistreatment. They may internalise the abuse as normal or deserved, leading to the development of a negative sense of self, including self-blame, feelings of unworthiness and the conviction that they are fundamentally “bad” (Naughton et al., 2013). This normality of abuse can also disrupt healthy attachment styles, resulting in resistant, avoidant attachment patterns that may continue into adulthood, making it difficult for them to form interpersonal relationships (Bailey et al., 2007).
Understanding the symptoms and reactions that a child possesses due to the difference in their trigger (acute vs. chronic) is beneficial in giving specialised treatment. Treatment methods can also be expanded when assessing the issue early, further helping children who suffer from PTSD.
The neuropsychological consequences of childhood trauma are equally significant. Research indicates that maltreated children demonstrate deficiencies in memory, attention, language, visuospatial skills, emotional regulation, social cognition and executive functioning (Barrera et al., 2013). In addition, the contrast between acute and chronic trauma carries profound implications for the risk of substance abuse, a comorbidity that has substantial long-term health consequences (Lortye et al., 2024). PTSD can manifest in an anxious and unstable state for the youth. A sense of impending danger can impinge on children’s ability to engage in developmentally appropriate tasks, taking on responsibilities well beyond a typical developmental stage, and/or disengaging from family, peers and school, becoming proactively aggressive in the belief that this is the only way to survive (Cohen, Mannarino & Deblinger, 2026). Furthermore, PTSD may also cause chronic impairments, leading to comorbid psychiatric illness and increased risk of suicide (Fariba & Gupta, 2024).
Childhood trauma profoundly affects future development and long-term health, and being able to differentiate between acute and chronic is critical as it shapes the severity of PTSD and overall psychological outcomes of patients. This review therefore asks: does acute versus chronic trauma in children produce distinct psychological outcomes, and does chronic trauma confer a greater risk of substance use disorders?
Comparison of Acute and Complex PTSD
From Acute Stress to Disorder: Understanding the Development and Treatment of Acute PTSD
Acute stress disorder (ASD) and PTSD are conditions that develop in the aftermath of exposure to a singular traumatic occurrence. Triggering incidents include, but are not limited to, circumstances that are unnerving and/or violent, a serious accident, natural disaster or assault (Cleveland Clinic, 2023), typically appearing within three days to one month after witnessing or involvement in the event (National Centre for PTSD, 2013; Cleveland Clinic, 2023). ASD is recognised as a precursor condition to PTSD, acting as the early but significant response to trauma before the disorder develops (World Health Organisation, 2023). Diagnostic criteria emphasise dissociative symptoms such as derealisation, the sense of being detached from one’s surroundings; depersonalisation, the feeling of being detached from oneself; and emotional numbing (Bryant & Harvey, 2000).
Both children and adults with ASD and PTSD often experience similar symptoms, including intrusive flashbacks, nightmares, avoidance of reminders, emotional numbness and heightened states of anxiety or arousal (DSM-IV, 1994). These symptoms can significantly disrupt daily life. It was found that in young adults aged 18-30 with a history of trauma, nightmares were significantly more frequent, leading to poorer sleep quality. As a result, participants reported memory lapses and concentration problems in everyday tasks and social functioning (Saranya et al., 2026). Thus, recognising ASD before it turns into PTSD is crucial due to its role in functioning as a warning sign and an early intervention opportunity.
The primary key distinction between ASD and PTSD is to do with timeframe: if severe symptoms persist longer than the stated period of one month, psychologists would classify the condition as PTSD; otherwise, it would be considered ASD. Furthermore, unlike ASD, PTSD has a higher prevalence in women (Johns Hopkins Psychiatry Guide, 2025). This may be credited to the fact that women are more likely to exhibit heightened hypothalamic-pituitary-adrenal (HPA) reactivity following trauma, which can intensify stress and increase the risk of PTSD (Yehuda et al., 1998). Individuals with poor social support and individuals with a high score of neuroticism in Eysenck’s personality questionnaire also share this risk. This trait predisposes individuals to interpret events more negatively and to experience stronger emotional reactions, which can exacerbate PTSD symptoms (Bramsen et al., 2000).
While adult patients with ASD often experience symptoms such as intrusive memories, nightmares, hypervigilance and avoidance behaviours (Dietiker et al., 2026), children may present differently. Instead of verbalising their mental distress, they may regress developmentally, such as bedwetting, thumb-sucking, clinginess and the display of somatic complaints such as stomach aches and headaches (Scheeringa & Zeanah, 2001; Meiser‑Stedman et al., 2008). They often show trauma-related memory fragmentation, difficulty concentrating and impaired executive functioning (De Bellis & Zisk, 2014). Children may also display aggression, irritability or withdrawal from peers (Pynoos et al., 1999). These behaviours are often misinterpreted as defiance rather than trauma responses. As juvenile patients have trouble articulating their own trauma, it is more common that they may display and seemingly “act out” their traumatic event through play as their own way of processing it (Terr, 1981).
While ASD and C-PTSD occurring after being exposed to repeated traumatic events share similar core responses to triggers, the main differences between the two are shown in the presence of DSO (disturbances in self-organisation). ASD is characterised by fear-based reactions tied to a single specific traumatic memory, leaving their personal identity intact, unlike complex PTSD, which is identity-based and can alter a person’s self-perception and view of the world.
Treatment is similar between children and adults, typically lasting for 8-16 weeks, with the end goal of successfully processing the traumatic memory to stop it from triggering the body’s panic response. The core therapy used during treatment primarily focuses on trauma-focused cognitive behavioural therapy (TF-CBT), with adult patient therapy being more independent and juvenile patients having heavier involvement with the child’s caregivers and a stronger focus on play. This process involves four main steps (see Figure 1).
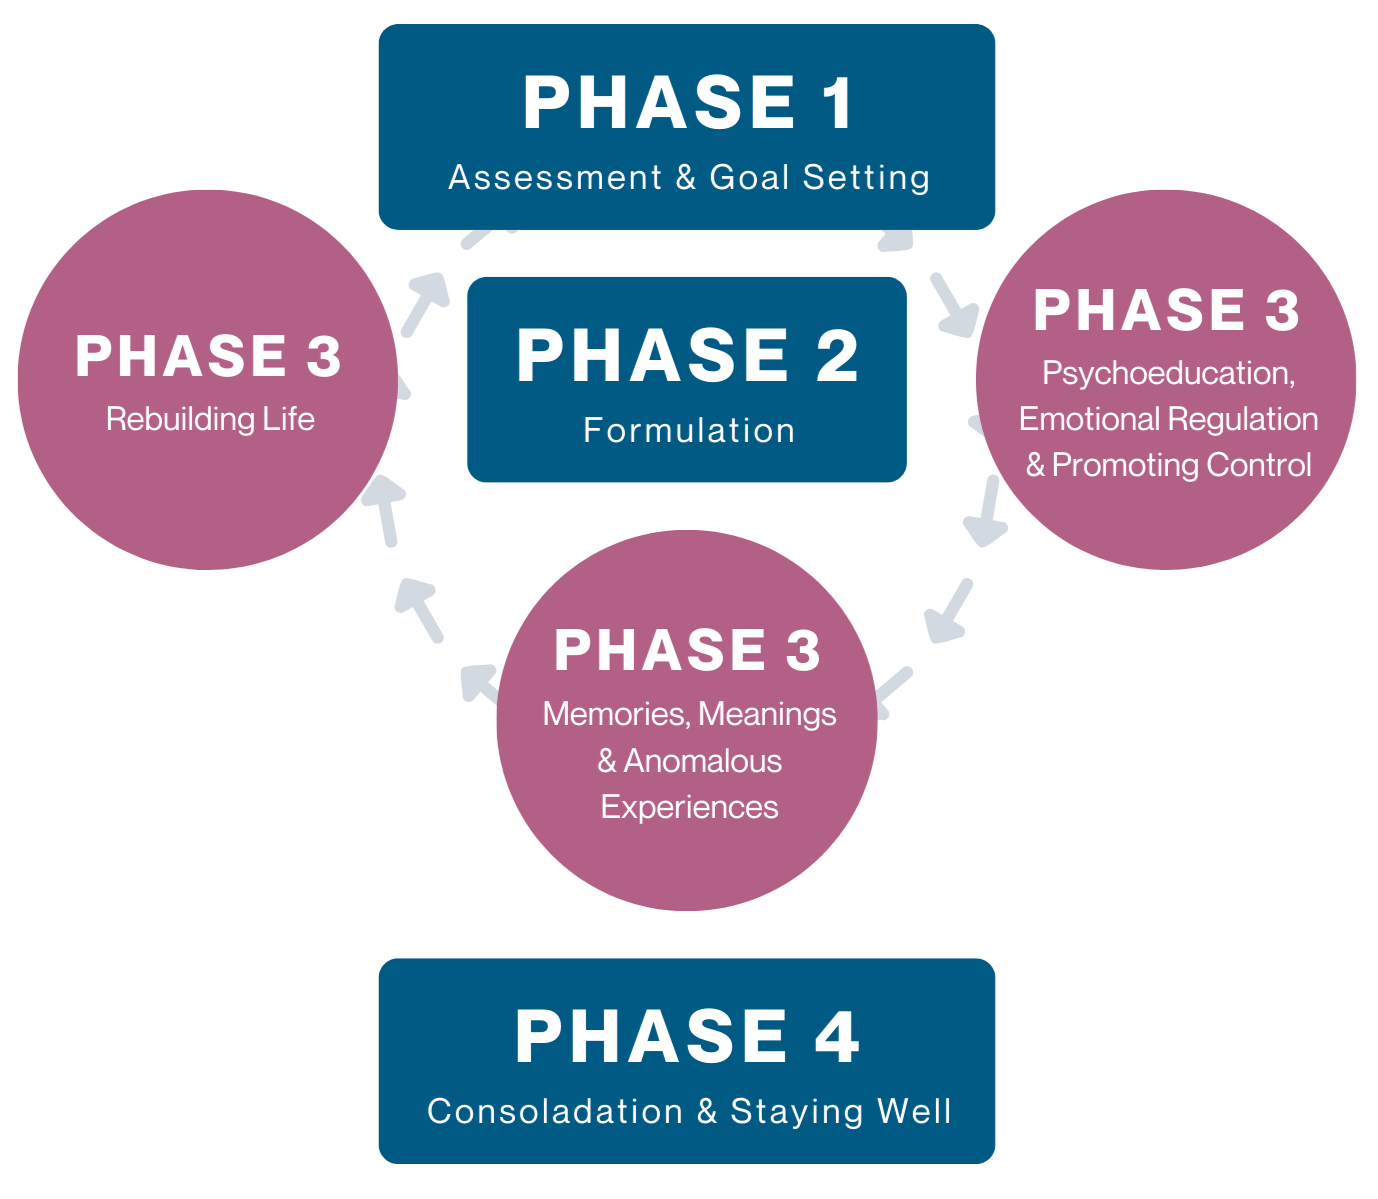
Figure 1. Healing from Trauma with Evidence-Based Therapy (Upper East Side Psychology, n.d.).
Complex PTSD: Chronic Trauma and Developmental Implications in Children
Complex post-traumatic stress disorder has been recognised by the ICD-11 as a new, discrete entity, distinct from PTSD and borderline personality disorder (BPD) (Stopyra et al., 2022). C-PTSD shares trauma-specific symptoms with its sibling disorder PTSD, but is additionally characterised by disturbances of the individual’s self-organisation (Nestgaard Rød & Schmidt, 2021). C-PTSD has symptom similarities to other disorders marked by emotional dysregulation, loss of consciousness, identity or self-control, such as dissociation disorders, depression, addiction and BPD (Cloitre, Garvert, Weiss, Carlson & Bryant, 2014; Ford, 2020). Although BPD and C-PTSD have a lot in common, they are expressed differently and have different motivations (Courtois & Ford, 2021). C-PTSD often gets misdiagnosed, and patients go through ineffective treatment (Evans, 2022). C-PTSD may occur following exposure to events that are traumatic (such events include torture, slavery, prolonged domestic violence and repeated childhood abuse). This means C-PTSD can arise from prolonged trauma and can also arise from a single event or experience (Stubley, Chipp & Buszewicz, 2025). Dr Judith Herman coined the term C-PTSD to describe the results in additional symptoms that have complex implications on the person’s relationships and sense of self – something that PTSD alone was criticised for overlooking (Landy et al., 2015).
If we look specifically at the diagnostic differences between PTSD and C-PTSD, we see additional symptoms that diagnose C-PTSD (on top of PTSD symptoms):
- Problems in affect regulation (such as marked irritability or anger, feeling emotionally numb);
- Beliefs about oneself as diminished, defeated or worthless, accompanied by feelings of shame, guilt or failure related to the traumatic event;
- Difficulties in sustaining relationships and in feeling close to others (Stubley, Chipp & Buszewicz, 2025).
The symptoms of C-PTSD cover not only fear- and horror-based responses but also the consequences that exposure to sustained, long term traumatic stressors can have on development, often tied to the deterioration of emotional and relational capacities (Ford, 2015; Hobfoll, Mancini, Hall, Canetti & Bonanno, 2011).
C-PTSD is strongly associated with what is known as chronic trauma: trauma that is repeated, lasting a prolonged period of time and usually happens in relationships or situations where you cannot escape or get help (DeCook and the Headway Clinical Team, 2026). The term ‘chronic’ or ‘complex’ trauma was formulated in the 1990s when researchers began to realise that some forms of trauma were much more pervasive and complicated than others. In children, it often involves the continuous experience of mistreatment, often in the context of an unsafe community (Berger, 2015). The difference between a single incident (acute) and chronic/complex trauma is that in single trauma incidents, the nervous system reacts only to one traumatic memory, making recovery simpler. On the other hand, ongoing trauma never allows the nervous system sufficient time to recover completely between events since the threat is consistent, so the body stays in an extended state of stress (Columbus Care Center, 2026). Children who live with family violence cannot rely on home as a safe base, and there is no escape from the physical or emotional reminders of previous scary incidents (Margolin & Vickerman, 2007). C-PTSD is commonly formed in early development, which can cause the child’s brain to become fully programmed for survival. This constant fear makes it difficult for their nervous system to self-regulate (Mulloy, 2019; Evans, 2022).
Chronic trauma and its strong association with C-PTSD has been characterised by its timing at crucial developmental phases and its destabilising of core elements of the self and one’s interpersonal relationships (Berger, 2015). Complex posttraumatic stress disorder can result from ongoing exposure to trauma, particularly in childhood. The trauma is frequently in the form of physical, emotional or sexual abuse perpetrated by those in a position of trust such as a parent or other relative, teacher, caregiver or clergyman (Franco, 2021). The main risk factor for C-PTSD identified was the experience of sexual abuse in childhood, with emotional neglect in childhood and being female as further significant risk factors (Stubley, Chipp & Buszewicz, 2025). When testing psychological developmental patterns in children who were abused, it was found that both emotional abuse and emotional neglect predicted relationship anxiety, relationship depression and fear of relationships (Dorahy et al., 2015). Children are particularly vulnerable when exposed to pervasive interpersonal traumas. They may not only develop PTSD but may undergo significant shifts that affect their biological, social, cognitive and emotional development: their experiences threaten their core beliefs as well as their sense of lovability, vulnerability and trust in family and friendships (Cruz et al., 2022). Due to the often repetitive and ongoing nature of family violence, many children in these situations meet the criteria for several disorders in addition to PTSD (Margolin & Vickerman, 2007). C-PTSD can lead to having a negative self-concept; it also includes feeling ineffective, completely alone and incapable of being understood (Evans, 2022). Children’s early relationships act as guidelines, and if their early relationships depict uncertainty and foster poor self-belief, their self-worth and identity can be destroyed (Teague, 2013; Downey & Crummy, 2021). Individuals with C-PTSD may be unable to separate themselves from their abuser physically, mentally and emotionally (Williams & Poijula, 2002; Evans, 2022). Interpersonal relationships contribute to a child’s general self-knowledge, and they may adopt familiar relationship patterns from their childhood in adulthood (Downey & Crummy, 2021).
Acute and Complex PTSD and the Risk of Addiction and Substance Abuse
How Do Trauma and Attachment Styles Contribute to Substance Use Disorders?
PTSD and alcohol use disorder (AUD) frequently co-occur and tend to exacerbate one another. Following trauma, PTSD symptoms decrease by approximately 50% within the first six months, with the greatest decline occurring soon after the event, indicating rapid initial symptom reduction (Hiller et al., 2016). Nevertheless, a substantial minority remain symptomatic and face increased risk of maladaptive coping. Trauma exposure can initiate a drinking-to-cope self-medication pathway, in which childhood trauma leads to PTSD symptoms and distress, which drives alcohol misuse to reduce distress; the temporary relief provided by drinking negatively reinforces this behaviour, making it more likely to recur (Hawn et al., 2020).
A mediation analysis found that depending on the severity of accumulated lifetime violence, alcohol abuse could be predicted in men with anxious attachment (Taylor et al., 2024), suggesting that attachment styles are not the sole determinants of substance abuse; the amount and severity of childhood and developmental adversity also matter. In a general population analysis, disorganised attachment (a highly insecure pattern combining anxious and avoidant behaviours) was associated with greater use of tranquilisers (e.g., sedatives, anti-depressants) and opioids (drugs like morphine) than avoidant, anxious and secure attachments, highlighting disorganised individuals’ particular vulnerability to sedatives (Fuchshuber, Löffler-Stastka & Unterrainer, 2025). Secure attachment protects against the impact of adverse childhood experiences (ACEs) on substance use disorders, whereas insecure attachment heightens risk, with substances often substituting for emotional voids stemming from early rejection, abuse or maltreatment (Levitin et al., 2026). Attachment insecurity is also linked to maladaptive personality traits connecting early adversity to adult relational patterns in people with substance use disorders.
Both acute and chronic childhood trauma significantly increase the risk for later substance use disorders (SUDs), but through distinct pathways that converge on similar addiction outcomes in adulthood. Acute, time-limited traumas often initiate a self-medication trajectory (Hawn et al., 2020; Hiller et al., 2016). However, chronic, repeated maltreatment more frequently disrupts attachment security and emotion-regulation systems, fostering insecure or disorganised attachment styles that make individuals more prone to use substances as substitutes for unmet relational and regulatory needs across their lifespan (Schindler, 2019; Tian et al., 2024). This pathway often begins in adolescence. Among individuals with comorbid PTSD and SUD, complex or chronic childhood trauma is significantly more prevalent, suggesting prolonged trauma strongly influences the PTSD-addiction comorbidity (Rakovski et al., 2025). Different forms of childhood maltreatment (e.g., physical abuse, sexual abuse, neglect) shape distinct attachment styles (like avoidant, anxious, disorganised styles), which in turn are linked to a higher likelihood of using particular drugs (Schindler, 2019; Levitin et al., 2026).
The distinction between acute and chronic trauma has important implications for substance-use risk, a comorbidity with long-term health consequences (Lortye et al., 2024). PTSD in youth can create a persistent sense of danger that disrupts developmentally appropriate tasks, leading to social withdrawal, premature assumption of adult responsibilities, aggressive coping, comorbid psychiatric illness and elevated suicide risk (Fariba & Gupta, 2024). Meta-analyses show that ACEs roughly double the odds of problematic alcohol use, heavy drinking, smoking, cannabis use and illicit drug use, with risk increasing alongside ACE number and severity (Lortye et al., 2024; Hughes et al., 2022). Another meta-analysis found that childhood maltreatment increases youth substance misuse by approximately fourfold, with 9 out of 10 maltreatment combinations showing a statistically significant association, indicating a broad and consistent link between maltreatment and substance misuse. Acute trauma instances contribute to addiction primarily through a distress-driven self-medication process, whereas chronic trauma does so through disrupted attachment and enduring emotion-regulation problems; both pathways frequently originate in childhood and elevate adult SUD risk (Hiller et al., 2016; Hawn et al., 2020; Tian et al., 2024).
The Relationship Between C-PTSD and Addiction in Youth
A study from the Addiction Research Institute in Ontario, Canada revealed that the earliest risk of onset use of alcohol began at ages 10-11, followed closely by prescribed drugs and hallucinogens within the next two years. Children face higher risks for experimentation with marijuana between the ages of 13-14, and the risk of initiation into hard drugs begins at around 15-16 (Hazelden Betty Ford Foundation, 2015). Children and adolescents with C-PTSD are approximately four times more likely to develop substance use disorder than their peers without C-PTSD, consistent with self-medication pathways in which substances are used to regulate trauma-related distress (Chilcoat & Breslau, 1998). Trauma is a common risk factor associated with SUDs; approximately 60% of youth with PTSD are affected (National Governors Association, 2025). This is because individuals who experienced chronic traumatic events may use substances to manage negative emotions surrounding PTSD symptoms (National Governors Association, 2025). Clinicians found that childhood adversity is linked to substances creating a temporary sense of safety, which is enhanced when the initial trauma was ongoing or repeated (Enlightened Recovery, 2025). Drug abuse or dependence in persons with PTSD can also be caused by efforts to self-medicate. C-PTSD affects many perceptions of control, escape and fundamental feelings of adequacy, which must be considered for effective rehabilitation (National Governors Association, 2025).
Additionally, addictive behaviours, described as behavioural addictions, can be defined as a process whereby a behaviour is employed in a pattern characterised by loss of control and continuation despite significant negative consequences. They are frequent and share many characteristics of SUDs such as tolerance, withdrawal and relapses (Blasco-Fontecilla et al., 2016). Regarding this, 30-50% of patients who suffer from disorders like anorexia nervosa or bulimia nervosa endorse excessive engagement in disordered behaviour or symptoms of dependence, which is done to create control or punishment, a common factor of SUD. This is rooted in abusive ideologies developed during chronic adversity; this idea of control also prompts self-harm. Eating disorders and self-harm are highly comorbid, with many individuals suffering from both (Barbarich-Marsteller, Foltin & Walsh, 2011). Studies have shown that self-inflicted harm is also commonly used as an outlet for escape, allowing trauma victims to release negative feelings temporarily, much like how people use substances. Those who engage in self-harming behaviours are also more likely to have SUD (Mahoney, 2018). Fundamentally, understanding amplified risks for SUD means noticing addictive behavioural patterns that can be intensified through C-PTSD before substance introduction to identify and prevent SUDs from developing.
Clinical research revealed that more than 40% of adults with PTSD also experience a SUD, with the two conditions reinforcing one another over time (Peltier et al., 2024). Evidence from a national survey in Japan involving over 1,000 adults with PTSD supports this relationship. Among participants, 61.8% reported substance abuse during the previous two weeks (Nagamine et al., 2023). Importantly, the researchers found that dissociative symptoms within patients predicted substance abuse within the following three months. Participants with a dissociative subtype of PTSD also demonstrated significantly higher levels of substance abuse than those without dissociative symptoms (Nagamine et al., 2023).
The development of SUD alongside PTSD can have significant consequences as individuals enter adulthood. Substance use may initially provide temporary relief from intrusive memories, anxiety, emotional distress or emotional numbness, but this effect is often short term (Ferrie et al., 2023). This reliance can create a cycle in which trauma-related distress encourages substance use, while substance use contributes to further psychological and physical difficulties. Consequently, the effects of PTSD and SUD may extend into education, employment, financial stability and interpersonal relationships, making it more difficult for individuals to establish a stable adult life (Hien et al., 2025).
Major depressive disorder (MDD) is also frequently associated with substance use, although the underlying mechanisms may differ from those observed in PTSD. Symptoms of depression are persistent sadness, low motivation, emotional numbness and difficulties with everyday activities (Sawchuk, 2022). Individuals may use alcohol or drugs as an attempt to temporarily regulate emotional distress. But often, substance use may intensify the depressive symptoms, creating a self-reinforcing cycle. A systematic review and meta-analysis of 48 articles involving 348,550 participants found that individuals with MDD had a 0.250 prevalence rate of also having a comorbid SUD, with alcohol use disorder being the most prevalent (Hunt et al., 2020). Bipolar disorder provides another example of how co-occurring psychiatric and substance use disorders can affect long-term health and functioning. A 2025 review reported that the lifetime prevalence of any SUD among individuals with bipolar disorder was 56.1%, compared with 13.8% in the general population. Several factors may contribute to this relationship, including impulsivity, changes in reward processing, mood instability and increased risk-taking during manic or hypomanic episodes. When bipolar disorder and SUD occur together, they are associated with more severe symptoms, a longer course of illness, higher suicide rates and greater overall health problems than when either condition occurs independently (Bonner-Reid et al., 2025). Both depression and bipolar disorder therefore demonstrate that when substance use develops alongside a psychiatric disorder, its consequences can extend beyond immediate symptoms and affect more severe illness, poorer social functioning and long-term health.
Discussion
Overall, we have found that there is a distinction in psychological consequences that stem from different sources of trauma. Acute trauma, singular traumatic instances, is less likely to lead to C-PTSD than chronic trauma is. C-PTSD is most often caused by recurrent, chronic or sustained trauma. C-PTSD has the clinical features of PTSD and symptoms that reflect the prolonged impact of sustained trauma on self-organisation, encompassing affect regulation, negative self-concept and difficulties sustaining interpersonal relationships (Stubley, Chipp and Buszewicz, 2025). Chronic trauma is more likely to lead to C-PTSD because there is not just one traumatic instance behind it; the pain is repeated and built into the lives of these individuals. The nervous system does not have time to heal, and the body is in a constant survival state (Centre, 2026). There is established evidence that the biggest risk factor for C-PTSD is ongoing childhood maltreatment (Omidbakhsh, Mohammadi & Soltanabadi, 2025). C-PTSD has several other implications aside from general PTSD symptoms. PTSD symptoms include intrusive memories, nightmares, hypervigilance and avoidance behaviours (Dietiker et al., 2026). C-PTSD also has psychological implications, including affective dysregulation, a negative sense of self including feelings of shame, guilt and worthlessness, and additionally severe difficulty in forming and maintaining meaningful relationships (Cleveland Clinic, 2023).
Distinguishing the root cause behind a patient’s PTSD – acute versus chronic – is important to understand because if a patient has been exposed to chronic trauma, they are more likely to have C-PTSD than PTSD, and C-PTSD covers a diverse cluster of symptoms that PTSD does not include (Resick et al., 2012). If C-PTSD and chronic trauma are recognised as distinct from normal PTSD, then clinicians and psychologists may be able to recognise the additional behavioural symptoms as part of the C-PTSD condition – not mislabel the behaviours and treat them as part of a different disorder, or treat only the recognised PTSD symptoms and ignore other possible consequences of the ongoing harm of C-PTSD. Although treatment for PTSD and C-PTSD is similar in that they both recommend trauma-focused intervention, C-PTSD requires a longer course of treatment and typically requires intervention focused on disturbances in self-organisation, something PTSD treatment itself does not cover (Cloitre, 2021).
Conclusion
After exploring the effects of adverse childhood experiences, differentiating between acute and chronic trauma is essential for understanding PTSD and C-PTSD in children. Acute trauma prompts an immediate, fear-based response often resolved with a prompt intervention, whereas chronic trauma alters a child’s identity, disrupts emotional regulation and heightens attachment issues. This prolonged exposure increases the risk of substance use disorders, as both acute and chronic trauma encourage maladaptive coping strategies, though in different ways: acute trauma often leads to self-medication behaviours, whereas chronic trauma destabilises a child’s attachment security and mood control long-term.
Evidence repeatedly shows that children with C-PTSD are increasingly likely to develop addictions and engage in harmful behaviours. As treatment must address both trauma symptoms and autonomic disturbances, being able to differentiate between them is a diagnostic necessity. Tailoring care protects children from long-term behavioural issues, emphasising the need for trauma-specific care, and by recognising the unique risks raised, clinicians, educators and caregivers are able to better support children in breaking cycles of harm while also nurturing resilience.
However, many barriers and limitations persist. While the World Health Organisation recognises C-PTSD as its own distinct condition and diagnosis, the American Psychiatric Association DSM-5-TR does not, instead categorising it under the broader PTSD umbrella. This inconsistent global diagnostic criteria leaves clinicians without a clearly defined framework, easily leading to misdiagnosis as the DSO states that those with C-PTSD symptoms overlap with BPD patients. Care patients receive is equally limited, often requiring longer-term therapy, which is costly and will likely not be covered by standard insurance, preventing proper care.
To bridge these gaps and improve care, it is crucial that systemic changes be implemented, such as updating medical training for C-PTSD or implementing universal diagnostic criteria, which are necessary to ensure a more accurate diagnosis and treatment, subsequently protecting patients from misdiagnosis and lack of proper treatment.
Bibliography
Adams, Z.W., McCauley, J.L., Back, S.E., Flanagan, J.C., Hanson, R.F., Killeen, T.K. and Danielson, C.K. (2016) ‘Clinician Perspectives on Treating Adolescents with Co-occurring Post-Traumatic Stress Disorder, Substance Use, and Other Problems’, Journal of Child & Adolescent Substance Abuse, 25(6), pp. 575-583.
American Psychiatric Association (1994) Diagnostic and Statistical Manual of Mental Disorders, 4th edn (Washington, DC: American Psychiatric Association).
Athena D.F. Sherman, Balthazar, M., Zhang, W., Febres-Cordero, S., Clark, K. D, Klepper, M., Coleman, M. and Kelly, U. (2023) ‘Seeking safety intervention for comorbid post‐traumatic stress and substance use disorder: A meta‐analysis’, Brain and Behavior, 13(5).
Avery Lane (2025) Invisible Scars: The Overlooked Link Between Emotional Abuse and Addiction [online]. <https://averylanewomensrehab.com/invisible-scars-overlooked-link-between-emotional-abuse-addiction/>
Bailey, H.N., Moran, G. and Pederson, D.R. (2007) ‘Childhood maltreatment, complex trauma symptoms, and unresolved attachment in an at-risk sample of adolescent mothers’, Attachment & Human Development, 9(2), pp. 139-161.
Barbarich-Marsteller, N.C., Foltin, R.W. and Walsh, B.T. (2011) ‘Does anorexia nervosa resemble an addiction?’, Current Drug Abuse Reviews, 4(3), pp. 197–200.
Blasco-Fontecilla, H., de Leon, J., Baca-Garcia, E. and Oquendo, M.A. (2016) ‘Addictive behaviors and personality traits in adolescents’, Journal of Behavioral Addictions, 5(2), pp. 1-9.
Bonner-Reid, F.T., Dar, A., Zerin, A., Mishra, A.P., Lollobattista, C., Narasimhan, N., Desai, S. and Singh, S. (2025) ‘Comprehensive Review on Association of Bipolar Disorder and Substance Abuse: Dual Diagnosis and Treatment Approaches’, Cureus.
Bowen, A.M., Calder, R., Neale, J., Meynen, T. and Gilchrist, G. (2024) ‘Emotion Regulation in the Association Between Posttraumatic Stress Disorder and Substance Use: A Systematic Review With Narrative Synthesis’, Trauma Violence & Abuse.
Bramsen, I., Dirkzwager, A.J.E. and van der Ploeg, H.M. (2000) ‘Predeployment personality traits and exposure to trauma as predictors of posttraumatic stress symptoms: A prospective study of former peacekeepers’, American Journal of Psychiatry, 157(7), pp. 1115-1119.
Bramsen, I., van der Ploeg, H.M., van der Kamp, L.J.T. and Adèr, H.J. (2002). ‘Exposure to traumatic war events and neuroticism’, Personality and Individual Differences, 32(4), pp.747–760.
Bryant, R.A. and Harvey, A.G. (2000) Acute Stress Disorder: A Handbook of Theory, Assessment, and Treatment (Washington, DC: American Psychological Association).
Columbus Care Center (2026) ‘Difference Between Single-Incident Trauma and Chronic Trauma’, The Care Center [online]. <https://columbuscarecenter.com/2026/01/13/the-difference-between-single-incident-trauma-and-chronic-trauma/>
Chilcoat, H.D. and Breslau, N. (1998) ‘Posttraumatic Stress Disorder and Drug Disorders’, Archives of General Psychiatry, 55(10), p. 913.
Cleveland Clinic (2023) ‘CPTSD (Complex PTSD)’ [online]. <https://my.clevelandclinic.org/health/diseases/24881-cptsd-complex-ptsd>
Cloitre, M. (2021) ‘Complex PTSD: assessment and treatment’, European Journal of Psychotraumatology, 12(sup1), 1866423.
Cloitre, M., Hyland, P., Bisson, J.I., Brewin, C.R., Roberts, N.P., Karatzias, T. and Shevlin, M. (2019) ‘ICD‐11 Posttraumatic Stress Disorder and Complex Posttraumatic Stress Disorder in the United States: A Population‐Based Study’, Journal of Traumatic Stress, 32(6).
Cohen, J.A., Mannarino, A.P. and Deblinger, E. (2017) Treating Trauma and Traumatic Grief in Children and Adolescents, 2nd ed (New York: The Guildford Press).
Cohen, J.A. and Scheeringa, M.S. (2009) ‘Post-traumatic stress disorder diagnosis in children: Challenges and recommendations’, Dialogues in Clinical Neuroscience, 11(1), pp. 47-58.
Courtois, C.A. and Ford, J.D. (2021) Treating Complex Traumatic Stress Disorders in Adults: Scientific Foundations and Therapeutic Models, 2nd edn (New York: Guilford Press).
Cruz, D., Lichten, M., Berg, K. and George, P. (2022) ‘Developmental trauma: Conceptual framework, associated risks and comorbidities, and evaluation and treatment’, Frontiers in Psychiatry, 13(1), pp. 1–14.
De Bellis, M.D. and Zisk, A. (2014) ‘The biological effects of childhood trauma’, Child and Adolescent Psychiatric Clinics of North America, 23(2), pp. 185-222.
DeCook, R. and the Headway Clinical Team (2026) ‘PTSD vs. CPTSD: Understanding the differences’ [online]. <https://headway.co/mental-health-resources/ptsd-vs-cptsd>
D’Elia, D., Carpinelli, L. and Savarese, G. (2022). ‘Post-traumatic play in child victims of adverse childhood experiences: A pilot study with the MCAST—Manchester child attachment story task and the coding of PTCP markers’, Children, 9(12), 1991.
Dietiker, C., Meiser-Stedman, R. and Birmes, P. (2026) ‘Acute stress disorder in children and adolescents: A systematic review’, European Journal of Psychotraumatology, 17(1), pp. 1-15.
Dietiker, L., Zacher, A., de’Sperati, S., Loosli, M., Schmid, L.B., Wernigg, M., Rühlmann, C., Bavato, F., Zölch, N., Seifritz, E., Quednow, B.B. and Kleim, B. (2026). ‘Attenuating trauma- and cocaine-related intrusions by blocking memory reconsolidation with minocycline: Protocol for a transdiagnostic randomized controlled trial’, European journal of psychotraumatology, 17(1).
Dorahy, M.J., Middleton, W., Seager, L., Williams, M. and Chambers, R. (2015) ‘Child abuse and neglect in complex dissociative disorder, abuse-related chronic PTSD, and mixed psychiatric samples’, Journal of Trauma & Dissociation, 17(2), pp. 223–236.
Downey, L. and Crummy, A. (2021) ‘The impact of childhood trauma on adult attachment and relationships’, Journal of Trauma & Dissociation, 22(4), pp. 456-472.
Enlightened Recovery (2025) ‘Understanding the link between childhood trauma and substance abuse’, Enlightened Recovery Blog [online]. <https://enlightenedrecovery.com/trauma-and-addiction-unearthing-your-hidden-emotions/>
eSkyCityDEVRG (2020) ‘The Connection Between Childhood Trauma Adult Addiction’, Old Vineyard Behavioral Health Services [online]. <https://oldvineyardbhs.com/blog/connection-between-childhood-trauma-addiction/>
Evans, L. (2022) ‘Complex Post Traumatic Stress Disorder – What is it?’, The Meliorist [online]. <https://themeliorist.ca/2022/11/28/complex-post-traumatic-stress-disorder/>
Fariba, K. and Gupta, V. (2024) ‘Posttraumatic Stress Disorder In Children’, StatPearls (Treasure Island (FL): StatPearls Publishing).
Ferrie, M.L., Lheureux, A., Vujanovic, A.A., Zvolensky, M.J. and Raines, A.M. (2023) ‘Co-Occurring Posttraumatic Stress Disorder Symptoms and Alcohol Use Behaviors: The Mediating Role of Drinking to Cope with PTSD Symptoms’, Journal of Dual Diagnosis.
Ford, J.D. (2015) ‘Complex trauma and complex posttraumatic stress disorder’, in Friedman, M.J., Keane, T.M. and Resick, P.A. (eds.) Handbook of PTSD: Science and Practice, 2nd edn (New York: Guilford Press), pp. 411-440.
Ford, J.D. (2020) ‘Posttraumatic stress disorder and complex posttraumatic stress disorder’, in The Wiley Encyclopedia of Health Psychology.
Franco, F. (2021) ‘Understanding and treating C-PTSD’, Journal of Health Service Psychology, 47(2), pp. 85–93.
Fuchshuber, J., Löffler-Stastka, H. and Unterrainer, H.F. (2025) ‘Attachment styles and substance use preferences in the general population’, Journal of Psychiatric Research, 178, pp. 45-52.
Fung, H.W., Huang, C.H.O., Cheung, C.T.Y., Chou, P.-H. and Ito, M. (2025) ‘Dissociation and substance abuse among people with PTSD: Results from the National Survey for Stress and Health in Japan’, Asian Journal of Psychiatry, 105, 104394.
Hartley, T.A., Sarkisian, K., Violanti, J.M., Andrew, M.E. and Burchfiel, C.M. (2016). PTSD symptoms among police officers: Associations with frequency, recency, and types of traumatic events. International journal of emergency mental health, 15(4), 241.
Hawn, S.E., Cusack, S.E. and Amstadter, A.B. (2020) ‘A systematic review of the self‐medication hypothesis in the context of posttraumatic stress disorder and comorbid problematic alcohol use’, Journal of Traumatic Stress, 33(5).
Hazelden Betty Ford Foundation (2015) ‘When Do People Start Using Alcohol and Drugs’ [online]. <https://www.hazeldenbettyford.org/articles/when-do-people-start-using-alcohol-and-drugs>
Hendren, R.L. and McCarthy, J. (2009) ‘Posttraumatic stress disorder in children and adolescents’, Dialogues in Clinical Neuroscience, 11(1), pp. 37-45.
Hien, D.A., Gette, J.A., Blakey, S.M., Piccirillo, M.L., Back, S.E., Bauer, A.G., Ebrahimi, C.T., Ellis, R.A., Killeen, T.K., Lehinger, E.A., López‐Castro, T., Norman, S.B., Ruglass, L.M., Saraiya, T.C., Saavedra, L.M. and Morgan‐López, A.A. (2025) ‘How changes in posttraumatic stress disorder (PTSD) severity mediate substance use disorder (SUD) severity during and after treatment for co‐occurring PTSD and SUD: Results from Project Harmony’, Addiction.
Hiller, R.M., Meiser-Stedman, R., Fearon, P., Lobo, S., McKinnon, A., Fraser, A. and Halligan, S.L. (2016) ‘Research Review: Changes in the prevalence and symptom severity of child post-traumatic stress disorder in the year following trauma – a meta-analytic study’, Journal of Child Psychology and Psychiatry, 57(8), pp. 884–98.
Hobfoll, S.E., Mancini, A.D., Hall, B.J., Canetti, D. and Bonanno, G.A. (2011) ‘The limits of resilience: Distress following chronic political violence among Palestinians’, Social Science & Medicine, 72(8), pp. 1400-1408.
Hordvik, E. (2019) What is Psychological Trauma? Routledge eBooks, pp. 23–30.
Hughes, K., Bellis, M.A., Hardcastle, K.A., Sethi, D., Butchart, A., Mikton, C., Jones, L. and Dunne, M.P. (2022) ‘The effect of multiple adverse childhood experiences on health: a systematic review and meta-analysis’, The Lancet Public Health, 7(7), e604-e615.
Hunt, G.E., Malhi, G.S., Lai, H.M.X. and Cleary, M. (2020) ‘Prevalence of comorbid substance use in major depressive disorder in community and clinical settings, 1990–2019: Systematic review and meta-analysis’, Journal of Affective Disorders, 266(1), pp. 288–304.
Johns Hopkins Psychiatry Guide (2025) Posttraumatic stress disorder (PTSD) [online]. <https://www.hopkinsguides.com/hopkins/view/Johns_Hopkins_Psychiatry_Guide/787066/7/Post_Traumatic_Stress_Disorder>
Landy, M.S.H., Wagner, A.C., Brown-Bowers, A. and Monson, C.M. (2015) ‘Examining the Evidence for Complex Posttraumatic Stress Disorder as a Clinical Diagnosis’, Journal of Aggression, Maltreatment & Trauma, 24(3), pp. 215–236.
Levitin, S., Kram, R. and Cohen, J. (2026) ‘Attachment security as a protective factor against substance use in maltreated children’, Child Abuse & Neglect, 125, 105452.
Lortye, S.A., Will, J.P., Rameckers, S.A., Marquenie, L.A., Goudriaan, A.E., Arntz, A. and de Waal, M.M. (2024) ‘Types of childhood maltreatment as predictors of posttraumatic stress disorder severity and complex posttraumatic stress disorder in patients with substance use disorders’, European Journal of Psychotraumatology, 15(1), 2367179.
Mahoney, B. (2018) ‘Teenage Addiction and Self-Harm: Co-occurring Disorders’, Discovery Mood & Anxiety Program [online]. <https://discoverymood.com/blog/teenage-addiction-self-harm-co-occurring-disorders/>
Margolin, G. and Vickerman, K.A. (2007) ‘Posttraumatic stress in children and adolescents exposed to family violence: I. Overview and issues’, Professional Psychology: Research and Practice, 38(6), pp. 613–619.
Meiser-Stedman, R., Dalgeish, T., Smith, P., Glucksman, P. and Yule, W. (2008) ‘Parent and child agreement for acute stress disorder, post-traumatic stress disorder and other psychopathology in a prospective study of children and adolescents exposed to single-event trauma’, APA [online]. <https://psycnet.apa.org/record/2008-00362-005>
Meiser-Stedman, R., McKinnon, A., Dixon, C., Boyle, A., Smith, P. and Dalgleish, T. (2017) ‘Acute stress disorder and the transition to posttraumatic stress disorder in children and adolescents: Prevalence, course, prognosis, diagnostic suitability, and risk markers’, Depression and Anxiety, 34(4), pp. 348–355.
Meiser-Stedman, R., Smith, P., Glucksman, E., Yule, W. and Dalgleish, T. (2008) ‘The posttraumatic stress disorder diagnosis in preschool- and elementary school-age children exposed to motor vehicle accidents’, American Journal of Psychiatry, 165(10), pp. 1326-1337.
Mental Health Center (2026) ‘Understanding Complex PTSD and How It Differs From PTSD’ [online]. <https://www.mentalhealthctr.com/understanding-complex-ptsd-and-how-it-differs-from-ptsd/>
Mok, A., Douflias, C. and Lena (2025) ‘A biobank for complex post-traumatic stress disorder (C-PTSD) and PTSD: study protocol for a cross-sectional study’, European Journal of Psychotraumatology, 16(1).
Mulloy, J. (2019) ‘The neurobiology of childhood trauma and its impact on development’, Journal of Child & Adolescent Trauma, 12(3), pp. 345-356.
Nagamine, M., Yamamoto, T. and Takahashi, Y. (2023) ‘Dissociative symptoms and substance abuse in PTSD: A national survey in Japan’, Journal of Traumatic Stress, 36(4), pp. 789-798.
National Center for PTSD (2013) ‘Acute stress disorder’. U.S. Department of Veterans Affairs [online]. <https://www.ptsd.va.gov/>
National Governors Association (2025) ‘Addressing The Link Between Trauma And Addiction’ [online]. <https://www.nga.org/publications/addressing-the-link-between-trauma-and-addiction/>
Naughton, A.M., Maguire, S.A., Mann, M.K., Lumb, R.C., Tempest, V., Gracias, S. and Kemp, A.M. (2013) ‘Emotional, behavioral, and developmental features indicative of neglect or emotional abuse in preschool children: A systematic review’, JAMA Pediatrics, 167(8), pp. 769-775.
Nestgaard Rød, Å. and Schmidt, C. (2021) ‘Complex PTSD: what is the clinical utility of the diagnosis?’, European Journal of Psychotraumatology, 12(1).
Omidbakhsh, Z., Mohammadi, Z. and Soltanabadi, S. (2025) ‘Childhood Maltreatment and Complex PTSD: A Systematic Literature Review’, Trauma, Violence, & Abuse.
Online Expat Counseling for individuals and couples (2025) ‘Complex PTSD, PTSD and PTS explained and compared’ [online]. <https://barendspsychology.com/complex-ptsd/>
Olff, M., Güzelcan, Y., de Vries, G.-J., Assies, J. and Gersons, B.P.R. (2006). HPA- and HPT-axis alterations in chronic posttraumatic stress disorder. Psychoneuroendocrinology, 31(10), pp.1220–1230.
Peltier, M.R., Verplaetse, T.L., Altemus, M., Zakiniaeiz, Y., Ralevski, E.A., Mineur, Y.S., Gueorguieva, R., Picciotto, M.R., Cosgrove, K.P., Petrakis, I. and McKee, S.A. (2024) ‘The role of neurosteroids in posttraumatic stress disorder and alcohol use disorder: A review of 10 years of clinical literature and treatment implications’, Frontiers in Neuroendocrinology, 73, 101119.
PTSD UK (n.d.) ‘Symptoms of PTSD and C-PTSD in children and young adults’ [online]. <https://www.ptsduk.org/symptoms-of-ptsd-in-children-and-young-adults/>
Pynoos, R.S., Steinberg, A.M. and Piacentini, J.C. (1999) ‘A developmental psychopathology model of childhood traumatic stress and intersection with anxiety disorders’, Biological Psychiatry, 46(11), pp. 1542-1554.
Rakovski, C., Lalli, M., Gu, J., Hobson, M., Wollenhaupt-Aguiar, B., Minuzzi, L., Flavio Kapczinski, de, T. and Frey, B.N. (2024) ‘Childhood maltreatment as a predictor of substance use/misuse among youth: A systematic review and meta-analysis’, Neuroscience & Biobehavioral Reviews, 166, 105873.
Resick, P.A., Bovin, M.J., Calloway, A.L., Dick, A.M., King, M.W., Mitchell, K.S., Suvak, M.K., Wells, S.Y., Stirman, S.W. and Wolf, E.J. (2012) ‘A critical evaluation of the complex PTSD literature: Implications for DSM-5’, Journal of Traumatic Stress, 25(3), pp. 241–251.
Saranya, R., Kumar, A. and Singh, P. (2026) ‘Nightmares, sleep quality, and cognitive functioning in young adults with trauma history’, Sleep Medicine, 120, pp. 45-53.
Saranya, T.S., Soloman, S.M., Gupta, S.K., Yucel, S. and Yucel, R. (2026) The impact of trauma on sleep quality: Examining the role of nightmares in cognitive impairment. Annals of Neurosciences.
Sawchuk, C. (2022) ‘Depression (Major Depressive Disorder)’, Mayo Clinic [online]. <https://www.mayoclinic.org/diseases-conditions/depression/symptoms-causes/syc-20356007>
Scheeringa, M.S. and Zeanah, C.H. (2001) ‘A relational perspective on PTSD in early childhood’, Journal of Traumatic Stress, 14(4), pp. 799-815.
Scheidell, J.D., Quinn, K., McGorray, S.P., Frueh, B.C. and Khan, M.R. (2018) ‘Childhood traumatic experiences and the association with marijuana and cocaine use in adolescence through adulthood’, Addiction, 113(1), pp. 44-56.
Schindler, A. (2019) ‘Attachment and substance use disorders: Theoretical models, empirical evidence, and implications for treatment’, Frontiers in Psychiatry, 10, p. 727.
Scoglio, A.A.J., Reilly, E.D., Girouard, C., Quigley, K.S., Carnes, S. and Kelly, M.M. (2020) ‘Social Functioning in Individuals With Post-Traumatic Stress Disorder: A Systematic Review’, Trauma, Violence, & Abuse, 23(2), 152483802094680.
Sperry, S.H. and Lippard, E.T.C. (2025) ‘Co-Occurring Bipolar and Substance Use Disorders: A Review of Impacts, Biopsychosocial Mechanisms, Assessment, and Treatment’, Focus, 23(2), pp. 173–182.
Stopyra, M.A., Simon, J.J., Rheude, C. and Nikendei, C. (2022) ‘Pathophysiological aspects of complex PTSD – a neurobiological account in comparison to classic posttraumatic stress disorder and borderline personality disorder’, Reviews in the Neurosciences.
Stubley, J., Chipp, B. and Buszewicz, M. (2025) ‘Diagnosis and management of complex post-traumatic stress disorder (C-PTSD)’, BMJ, e079458.
Taylor, C., Smith, P. and Jones, L. (2024) ‘Accumulated lifetime violence, attachment anxiety, and alcohol abuse in men’, Addiction Research & Theory, 32(1), pp. 55-63.
Teague, R. (2013) ‘Attachment and the developing child’, Journal of Child and Adolescent Psychiatric Nursing, 26(4), pp. 230-238.
Terr, L.C. (1981) ‘Forbidden games: Post-traumatic child’s play’, Journal of the American Academy of Child Psychiatry, 20(4), pp. 741-760.
Tian, Y., Liu, Y. and Zhang, L. (2024) ‘Childhood trauma, attachment styles, and substance use: A longitudinal study’, Addiction Research & Theory, 32(2), pp. 112-125.
UES Psychology (2017) ‘Trauma-Focused Cognitive Behavioral Therapy’ [online]. <https://www.uppereastsidepsychology.com/therapeutic-approaches-1/trauma-focused-cbt-%2528tf-cbt%2529>
Williams, M.B. and Poijula, S. (2002) The PTSD Workbook: Simple, Effective Techniques for Overcoming Traumatic Stress Symptoms (Oakland, CA: New Harbinger Publications).
Within Health (2025) ‘Understanding Self-Harm and Eating Disorders’ [online]. <https://withinhealth.com/learn/articles/self-harm-and-eating-disorders>
World Health Organization (2023) International Classification of Diseases for Mortality and Morbidity Statistics, 11th edn.
Yehuda, R., McFarlane, A.C. and Shalev, A.Y. (1998) ‘Predicting the development of posttraumatic stress disorder from the acute response to a traumatic event’, Biological Psychiatry, 44(12), pp. 1305-1313.